- Home/
- Buy Clomid Online in the United States – Fast Shipping Available
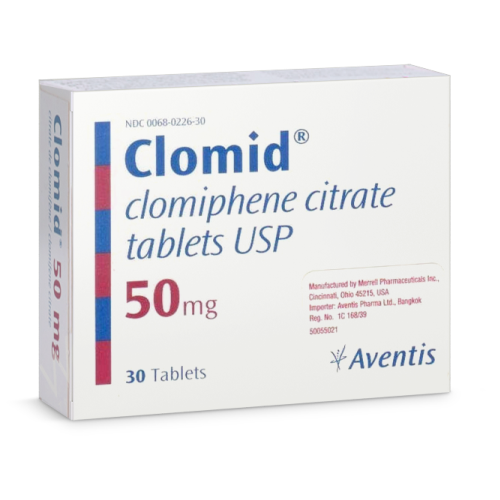
Deciding on Clomid: Not Always Plan A, But Often the Starting Line
Infertility rarely feels like a straight path. If you’re reading this, chances are you’ve spent months—or years—watching the calendar and waiting for a sign that your body is ready. When that sign doesn’t come, the search for answers leads many people to the word “Clomid.” Not because it’s a miracle, but because it’s often the first medication that brings the possibility of ovulation back into the conversation.
But Clomid isn’t handed out casually in the United States. It’s a prescription, not a supplement, and doctors wield it with clear intentions: Select patients—typically those with irregular or absent ovulation, such as in polycystic ovary syndrome (PCOS)—are considered ideal candidates. For those with blocked tubes, severe male factor infertility, or diminished ovarian reserve, Clomid is less likely to be the answer.
The right candidate, according to most American infertility specialists, is someone whose problem is an ovulatory glitch, not a structural or age-related barrier. The medication’s role? To gently nudge the hormonal system into producing and releasing a mature egg, turning a frustratingly blank ovulation test into a real chance each cycle.
Clomid isn’t always the first thing you try, but when it’s the right fit, it’s more about restoring a biological rhythm than rewriting the rules. The question that matters most here isn’t, “Will Clomid fix everything?” but “Is my infertility the kind Clomid is meant for?” If you don’t know, now is the time to ask your doctor.
How Clomid Acts on Your Body (And Why That Matters More Than the Science Says)
The story starts in your brain—not your ovaries. Clomid (clomiphene) is best known as a “selective estrogen receptor modulator,” but that jargon hides the real action: It tricks your body into thinking estrogen levels are low, signaling the brain’s command center (the hypothalamus) to ramp up the call for ovulation.
- Clomid binds to estrogen receptors in the brain, blocking the usual feedback that says, “We’ve got enough estrogen here.”
- Your brain responds with an alarm, increasing the release of GnRH (gonadotropin-releasing hormone).
- That, in turn, signals the pituitary gland to boost both FSH (follicle-stimulating hormone) and LH (luteinizing hormone).
- FSH and LH tell the ovaries: “Let’s mature and release an egg this month.”
That’s the textbook version. In real life, the response isn’t perfectly predictable. Some people respond on the first try. Others need a dose adjustment—or a different approach altogether. What matters most is that the signal to ovulate is rooted in your own hormonal pathways, not imposed from outside.
- Clomiphene:
- Stimulates ovulation by blocking estrogen feedback in the brain, leading to increased FSH and LH.
- Letrozole (an alternative):
- Reduces estrogen by inhibiting its synthesis, leading to a similar boost in FSH and LH but with lower anti-estrogenic effects on the uterus and cervix.
The clinical bottom line: Clomid asks your body to do what it’s built to do, with a nudge—not a shove. But not every body responds the same way. Understanding this mechanism is less about the science and more about setting realistic expectations: a chance, not a guarantee.
Taking Clomid: The Real Day-to-Day Experience
The first Clomid pill often feels momentous—hope in a small white tablet. But after the symbolism fades, the experience usually settles into a pattern. Most courses start on day 3, 4, or 5 of your menstrual cycle, with daily dosing for five days. The dose might be 50 mg, or sometimes higher if a previous cycle didn’t trigger ovulation.
What surprises many patients isn’t the act of taking the pill, but the anticipation and the waiting. Will I ovulate? Will I feel different? The answer: You might, but probably not dramatically. Most people tolerate Clomid without major issues, though some report hot flashes, mood swings, or bloating. For others, it’s almost a non-event physically until it’s time to track ovulation.
- Monitoring: You may use ovulation predictor kits, track cervical mucus, or have ultrasounds at your doctor’s office to confirm ovulation.
- Treatment cycles: Doctors in the U.S. typically limit Clomid to 3–6 cycles per patient. More cycles do not improve the odds and may increase risks.
- Pregnancy rates: About 60–80% of people with ovulatory infertility will ovulate with Clomid, and of those, roughly half will conceive over several cycles.
One important feature of the Clomid experience: It’s a partnership between you, your body, and your physician. Your response is tracked, doses adjusted, and expectations managed with each cycle.
If you don’t ovulate after several attempts, your doctor may switch strategies—which doesn’t mean Clomid failed, only that your biology is asking for a different conversation.
Which Side Effects Matter Most with Clomid—and When to Act
Side effects are the shadow that trails every medication, but with Clomid, it’s less about “Will I feel bad?” and more about “Which effects should I actually care about?” Most are mild and temporary—hot flashes, mood swings, headaches, a sense of bloating. These reflect Clomid’s anti-estrogen effect, not toxicity.
There’s a particular worry that comes up in every support group and internet forum: “What if Clomid causes ovarian hyperstimulation or worse, ovarian cysts?” The reality in U.S. practice is that serious complications are rare when doses are used as prescribed and cycles are monitored. Ovarian hyperstimulation syndrome (OHSS) is much less common with Clomid than with injectable fertility drugs.
Most side effects can be managed by adjusting the dose or timing, but some deserve immediate attention. The table below summarizes what to watch for—and when to pick up the phone.
| Side Effect | Frequency | When to Contact Your Doctor |
|---|---|---|
| Hot flashes | ~10–25% | If severe, persistent, or interfering with daily life |
| Headache | ~5–10% | If severe, persistent, or associated with vision changes |
| Bloating/abdominal discomfort | ~5–15% | If severe pain, rapid weight gain, or abdominal swelling develops (possible OHSS) |
| Vision changes | Rare (<2%) | Immediately discontinue Clomid and consult your doctor |
| Mood swings/irritability | ~10% | If symptoms are severe or impact mental health |
| Ovarian cysts | Uncommon | If pelvic pain, fullness, or irregular bleeding occur |
What’s not on this list: long-term cancer risk. Research to date does not show a significant increase in ovarian cancer for patients using standard Clomid cycles under medical supervision. But if you have a personal or family history of hormone-sensitive cancer, be sure to discuss with your doctor before starting.
Clomid vs. Alternatives: A Table for the Real-World Decision
“Is Clomid the only option?” is the unspoken question in most new consultations. The short answer: No. The longer answer: Clomid is often the starting point, but there are other tools—especially when you factor in cost, convenience, and individual response.
| Medication | Main Use | Mechanism | Typical Candidates | Effectiveness | Common Side Effects | Prescription/Access (US) | Cost (US, typical) |
|---|---|---|---|---|---|---|---|
| Clomid (clomiphene) | Ovulation induction in anovulatory infertility (esp. PCOS) | Blocks estrogen receptors in brain; increases FSH/LH | Women with irregular/no ovulation; normal ovarian reserve | 60–80% ovulate; ~10–12% pregnancy/cycle | Hot flashes, mood swings, visual changes, ovarian cysts | Prescription only; widely available in US pharmacies | $10–$50 per cycle (generic); brand higher |
| Letrozole (Femara) | Alternative ovulation induction; PCOS, Clomid-resistant cases | Aromatase inhibitor; lowers estrogen synthesis | Women not responding to Clomid; PCOS (increasingly first-line) | 60–80% ovulate; studies suggest higher pregnancy rate than Clomid in PCOS | Fatigue, headache, hot flashes; less cervical/uterine effect | Prescription only; US pharmacies | $20–$60 per cycle (generic) |
| Gonadotropins (injectables) | Ovulation induction for Clomid/letrozole failures; IVF | FSH/LH analogs; direct ovarian stimulation | Women not ovulating with oral agents, or with other infertility factors | Higher ovulation/pregnancy rates—but higher risk of multiples, OHSS | Injection pain, bloating, ovarian hyperstimulation | Prescription only; specialty pharmacies; requires monitoring | $1,000–$5,000+ per cycle |
The biggest takeaway: Clomid remains the simplest, lowest-cost, and least invasive option for many. Letrozole is increasingly favored for specific groups, such as women with PCOS, because of more favorable pregnancy rates and fewer anti-estrogenic effects on the uterus. Injectable gonadotropins are powerful but bring higher cost, complexity, and risk. Your doctor’s recommendation will depend on your diagnosis, prior treatment response, and, often, the practical realities of insurance coverage and access in the United States.
Making Clomid Happen: Prescription, Pharmacies, and Price in the United States
After the decision comes the logistics—and in the U.S., that means the pharmacy counter, not a supplement aisle or online quick-order. Clomid is strictly prescription-only. You cannot legally buy it over-the-counter or through unregulated online sources in the United States. The FDA regulates both brand and generic versions, and reputable pharmacies will require a valid prescription from a licensed healthcare provider.
Generic clomiphene citrate is widely available and significantly less expensive than the original brand-name version. Typical U.S. pharmacy prices range from $10–$50 per treatment cycle, depending on the dose and pharmacy. Some chain pharmacies offer further price reductions through discount programs. Mail-order pharmacies may offer convenience, but ensure the pharmacy is U.S.-licensed and legitimate.
- FDA:
- The United States Food and Drug Administration, which approves and regulates all prescription fertility medications.
- Brand vs. Generic:
- Both are considered clinically equivalent for ovulation induction; most U.S. doctors prescribe generics for cost reasons unless a specific brand is required by the patient’s insurance or clinical situation.
If you’re considering Clomid, your next move is a consultation with an OB/GYN or fertility specialist. In-person visits remain the norm for initial evaluation, but some clinics may offer telehealth for follow-up or refill discussions. Remember: U.S. law prohibits dispensing Clomid without a prescription, and online pharmacies that do not require one should be avoided for safety and legal reasons.
When Not to Take Clomid (And Why Your Doctor Might Say No)
- Are pregnant or suspect you might be
- Have liver disease (current or past significant liver dysfunction)
- Have unexplained abnormal uterine bleeding
- Have a hormone-sensitive cancer (such as breast, uterine, or ovarian cancer)
- Have an ovarian cyst not caused by polycystic ovary syndrome (PCOS)
- Are allergic to clomiphene or any component of the tablet
These absolute contraindications are non-negotiable—your doctor will screen for them before writing a prescription. But there are gray zones, too. Relative contraindications include significant pituitary or thyroid dysfunction (unless corrected), uncontrolled adrenal disorders, or other medical issues that could interact with the hormonal effects of Clomid.
Finally, Clomid simply won’t work—or may even delay the right treatment—in patients with blocked fallopian tubes, poor ovarian reserve, or partner infertility that’s not addressed. A thorough fertility evaluation is essential before starting, even if you’re eager to move forward.
Your Clomid Questions—Answered Honestly
- How long does it usually take to get pregnant on Clomid?
- For those who ovulate in response to Clomid, most pregnancies happen within the first three to six cycles. If you haven’t conceived after this period, your doctor will likely consider alternative treatments or further evaluation for other fertility issues.
- Is it safe to buy Clomid online?
- Only from licensed U.S. pharmacies with a valid prescription. Many online sources are unregulated or illegal. Ordering without a prescription is unsafe and illegal in the United States.
- Will Clomid increase my risk of twins?
- Yes, but the risk is modest. About 6–8% of pregnancies with Clomid result in twins, compared to about 1% in the general population. Triplets and higher-order multiples are rare but possible.
- Can I use Clomid if I have regular periods?
- Generally, if you’re ovulating regularly, Clomid may not improve your chances. It is most effective for people whose infertility is due to irregular or absent ovulation.
- What’s the difference between Clomid and letrozole?
- Both stimulate ovulation but work differently. Letrozole is often preferred for women with PCOS due to higher pregnancy rates and fewer side effects related to the uterine lining.
- Do I need to be monitored while taking Clomid?
- Yes. Most U.S. doctors recommend at least some monitoring—ovulation predictor kits, ultrasound, or blood tests—to confirm ovulation and minimize risks like ovarian cysts or over-stimulation.
- Does insurance cover Clomid and infertility treatment?
- Coverage varies widely. Most health plans in the U.S. do not cover Clomid for infertility, but some exceptions exist. Check your plan’s specific coverage or ask your fertility clinic to help verify benefits.
- Is there a maximum number of cycles I can take Clomid?
- Yes. Most experts recommend no more than 6 cycles due to diminishing returns and slightly increased long-term risks. If pregnancy hasn’t occurred by then, another treatment plan is usually advised.
“What I tell my patients is that Clomid is a fair first step, but it’s not a guarantee. Ovulation is only one part of the fertility puzzle. If the first few cycles don’t work, it’s a sign we need to look more broadly—not that you failed or did something wrong.”
References
- U.S. Food and Drug Administration (FDA)
- American Society for Reproductive Medicine (ASRM): Practice Committee Documents
- Mayo Clinic: Clomiphene for Infertility
- Infertility: Assessment and Treatment. American College of Obstetricians and Gynecologists (ACOG)
- Clomid Prescribing Information, Sanofi-Aventis U.S.
- PubMed: Clomiphene Meta-Analyses
- ClinicalTrials.gov: Clomiphene Studies
- WHO: Infertility Fact Sheet